

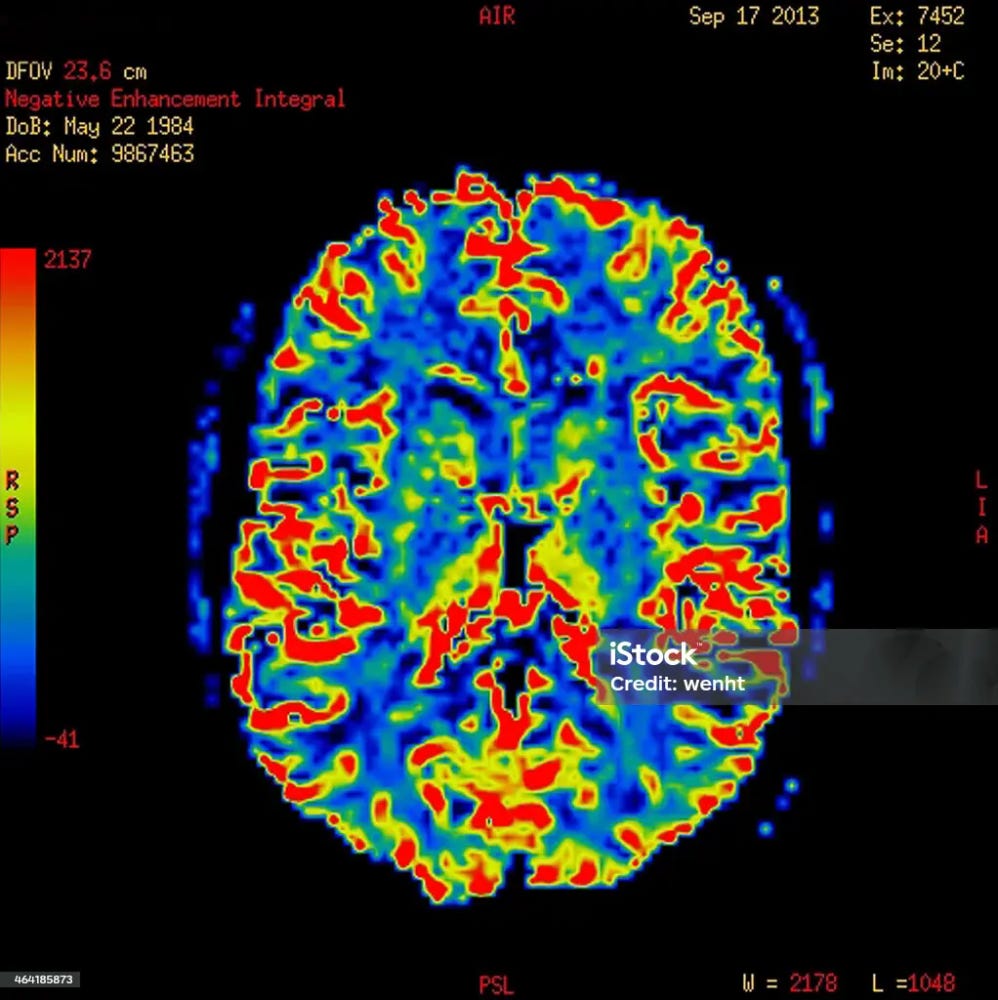
PTSD causes structural and functional brain changes, specifically an overactive alarm system (amygdala), a weakened rational control center (prefrontal cortex), and a damaged memory center (hippocampus). This combination causes the brain to stay in permanent “fight-or-flight” mode, creating intense fear, flashbacks, and difficulty distinguishing past trauma from present safety.
Key Brain Regions Affected Are:
Amygdala (Hyperactive): Acts as a hypersensitive alarm system, constantly detecting threats and triggering fear responses even in safe situations.
Prefrontal Cortex (Underactive): Responsible for rational thought, decision-making, and emotional regulation. In PTSD, this area is weakened, making it difficult to “put on the brakes” regarding fear reactions.
Hippocampus (Damaged/Smaller): Responsible for memory and context. A smaller, underactive hippocampus fails to differentiate between past trauma and present reality, leading to intrusive memories and flashbacks
PTSD & Depression Among Journalists Covering War
Professional Treatment Resources, Organizational Support, and Strategic Implications for the Journalism Community
Journalist imbedded with combat forces covering war carries risk. That has always been understood. The deeper issue, quietly discussed in newsrooms and among veteran correspondents, is whether the industry has fully recognized the strategic cost of the psychological injuries carried home by the journalists who document conflict for the rest of us.
After 24 years in clandestine, and Special operation forces, I medically retired, and upon the attacks on america on 9/11, I became the Senior Terrorism, and National Security Analyst, and Senior Producer, for the cable news network, and immediately deployed again to war, trading my weapons for cameras.
Not a fair trade.
For and additional two decades - my colleagues and I embedded with military units across Afghanistan, Iraq, the Horn of Africa, and other conflict zones. We have borne witness to violence on a scale few civilians encounter. The result is an emerging reality that editors and policy leaders are only beginning to acknowledge: war reporting has produced a generation of journalists carrying levels of trauma exposure comparable to the soldiers they deployed alongside. Having served in both professions, I concur with their findings.

There is also a historical lesson that institutions ignore at their own risk. After the Vietnam War the United States military spent years grappling with the delayed recognition of what later became widely known as post traumatic stress disorder among returning soldiers.
The Pentagons default position since its institutional inception has always been: Delay, Deny, Obfuscate, and make Counter Accusations. The did it with the Atomic Veterans, withholding health monitoring, Project SHAD (exposing biological agents to soldiers), Gulf War Illnesses, decades of denial, Havana Syndrome (blame the victim)/
Same with the CIA, and Havana Syndrome: Directed Energy Attacks on US officials, blame the victims, refuse service related compensation, until they finally covertly bought a weapon on the black market.
Winston Churchill said it best “The Americans can always be counted on to do the right thing, but only after they have expended all other options.”
The Pentagon eventually built an entire system of screening, treatment, and peer support to address those invisible injuries.
Journalism is now confronting a similar inflection point in both PTSD, and Havana Syndrome.

The profession has long focused on protecting reporters from bullets, kidnappings, and bombs. The strategic challenge now is protecting them from the long term psychological consequences of witnessing war itself.

Journalists covering war, terrorism, disasters, and mass violence operate in environments psychologically comparable to those experienced by soldiers and first responders. Research over the past two decades has demonstrated that repeated exposure to traumatic events produces measurable rates of post traumatic stress disorder, depression, anxiety disorders, and substance abuse within the profession.
A study published in The British Journal of Psychiatry examining journalists who covered wars in Afghanistan and Iraq between 2001 and 2013 found that approximately 27 percent met clinical criteria for PTSD compared with about 6 percent among journalists who had not covered war. Rates of depression and anxiety disorders were also significantly elevated.
These findings reinforce growing recognition inside major news organizations that war reporting is not only physically hazardous but psychologically hazardous as well.
A small but credible network of organizations has emerged to address these risks.
SECTION 1: The Most Respected Organizations Serving Trauma Exposed Journalists
Global Center for Journalism and Trauma (formerly Dart Center for Journalism and Trauma)
Overview The Global Center for Journalism and Trauma originally established at Columbia University is widely regarded as the leading global research and training institution focused on trauma exposure among journalists. The organization conducts research on PTSD among journalists trauma reporting practices newsroom psychological resilience and ethical coverage of violence and disasters.
Contact Information Website:
https://dartcenter.org
Email: dartcenter@columbia.edu Phone: +1 212 854 8056 Address: Global Center for Journalism and Trauma Columbia University Graduate School of Journalism 2950 Broadway New York NY 10027 United States
Journalist Trauma Support Network
Overview The Journalist Trauma Support Network connects journalists with clinicians trained specifically in trauma experienced by reporters photographers and documentary filmmakers. Programs include confidential counseling referrals trauma informed therapy and crisis counseling following traumatic assignments.
Contact Information Website:
https://www.jtsn.org
Email: info@jtsn.org Phone: +1 202 496 1992 Address: Journalist Trauma Support Network International Women’s Media Foundation 1625 K Street NW Suite 1275 Washington DC 20006 United States
Committee to Protect Journalists
Overview The Committee to Protect Journalists provides emergency support for journalists suffering trauma after violence imprisonment or attacks including trauma counseling referrals emergency financial support and relocation assistance.
Contact Information Website:
https://cpj.org
Email: emergency@cpj.org Phone: +1 212 465 1004 Address: Committee to Protect Journalists 330 Seventh Avenue New York NY 10001 United States
Rory Peck Trust
Overview The Rory Peck Trust provides trauma counseling grants psychological recovery programs safety training and emergency assistance to freelance reporters covering dangerous assignments.
Contact Information Website:
https://rorypecktrust.org
Email: info@rorypecktrust.org Phone: +44 20 3219 7860 Address: Rory Peck Trust 75 Wells Street 2nd Floor London W1T 3QH United Kingdom
International Women’s Media Foundation
Overview The International Women’s Media Foundation provides emergency assistance trauma counseling support safety training and mental health resources for women journalists working in high risk environments.
Contact Information Website:
https://www.iwmf.org
Email: info@iwmf.org Phone: +1 202 496 1992 Address: International Women’s Media Foundation 1625 K Street NW Suite 1275 Washington DC 20006 United States
Substance Abuse and Mental Health Services Administration SAMHSA
Overview SAMHSA operates a nationwide network of PTSD treatment resources and provides access to trauma specialists throughout the United States.
Contact Information Website:
https://www.samhsa.gov
National Helpline: +1 800 662 4357 Address: Substance Abuse and Mental Health Services Administration 5600 Fishers Lane Rockville MD 20857 United States
SECTION 2: Practitioner Perspective from a War Correspondent
For policymakers newsroom leaders and the public the implications are significant. War reporting is not simply a professional assignment. It is an operational environment in which journalists function as civilian witnesses embedded within military campaigns. Over time the accumulated exposure to combat destruction and human loss produces psychological consequences that can surface years later.
Beginning on the morning of September 11th, 2001, I started covering the global war on terrorism as a television journalist and combat embedded reporter. Within weeks I deployed to Afghanistan during the initial invasion following the attacks. That assignment began an eighteen year period covering war zones and military operations across the Middle East and South Asia.
During the opening phase of the Afghanistan campaign I reported from forward operating areas alongside US forces operating near the Durand Line and inside the tribal regions of what was then the North West Frontier Province. These deployments included time with US Army Special Forces units operating across the border region into Taliban controlled territory.
When the United States launched the invasion of Iraq in 2003 I shifted to the headquarters responsible for directing the ground war. I was the only television journalist assigned to cover the commanding generals running the campaign at Combined Forces Land Component Command headquarters known as CFLCC.

From that position I documented the operational planning and execution of the ground invasion of Iraq including the coordination between US Army formations, US Marine Expeditionary Units, and coalition forces moving north toward Baghdad.
Over the following years I continued reporting alongside multiple US military formations including the 5th Special Forces Group the 101st Airborne Division US Marine Expeditionary Units, Air Force Combat Control teams and units operating across the Durand Line into the tribal wild lands of the North West Frontier Province.
Those deployments ultimately produced multiple long form documentary reports examining the operational realities of modern warfare and the soldiers and Marines conducting those missions.
SECTION 3: Strategic Assessment
The deeper issue now confronting the journalism profession is institutional adaptation. War reporting remains essential to democratic societies. Without journalists documenting conflict the public would know far less about the consequences of decisions made in distant capitals.
But documenting violence carries long term psychological costs. Organizations such as the Dart Center the Journalist Trauma Support Network the Committee to Protect Journalists and the Rory Peck Trust represent the early stages of a mental health infrastructure for the profession.
If news organizations integrate trauma awareness into safety training pre deployment briefings and post assignment decompression programs the profession will become more sustainable. If those reforms stall the industry risks losing experienced war correspondents to burnout untreated PTSD and depression.
SECTION 4 – Stellate Ganglion Block (SGB): A Promising Treatment for PTSD
Among emerging medical treatments for post‑traumatic stress disorder, one of the most discussed in military and trauma medicine circles is the Stellate Ganglion Block (SGB) procedure. The technique has gained attention among veterans, first responders, and trauma‑exposed journalists because it can reduce PTSD symptoms rapidly in some patients.
The procedure has been strongly associated with the work of our special mission unit surgeon, Dr. Sean W. Mulvaney, a former U.S. Navy SEAL who later became a physician and researcher specializing in minimally invasive trauma treatments.
Special Mission Units were tested, and successfully treated using this method. I was an original prticipant in the first testing cohort, prior to peer review. The system works, you leave the procedure with a euphoric feeling of grace, and are then highly receptive to other traditional methods of psychology to tear the underlying cause of the trauma.
WHO IS DR. SEAN MULVANEY
Dr. Sean Mulvaney is a physician, former U.S. Navy SEAL, and former military doctor who spent more than three decades in military service before entering private medical practice. He is widely regarded as one of the leading clinicians researching the use of stellate ganglion block injections to treat combat‑related PTSD symptoms.
While serving in the military medical system, Mulvaney began exploring the use of stellate ganglion block injections to treat soldiers suffering from combat‑related trauma. His work helped expand interest in the procedure as a potential treatment for PTSD and anxiety disorders.
He later founded the SGB Treatment Center in Annapolis, Maryland, where he continues to treat patients and conduct research on trauma medicine.
WHAT THE STELLATE GANGLION BLOCK PROCEDURE DOES
The stellate ganglion is a bundle of sympathetic nerves located in the neck that regulates the body’s fight‑or‑flight response.
In patients suffering from PTSD, the nervous system can become chronically overstimulated, producing symptoms such as hypervigilance, anxiety, intrusive memories, insomnia, and exaggerated startle responses.
The SGB procedure attempts to interrupt this cycle.
During the treatment:
A physician injects a local anesthetic near the stellate ganglion nerve bundle in the side of the neck.
The injection temporarily blocks sympathetic nerve signaling.
This can reduce the over‑activation of the brain’s fight‑or‑flight circuitry.
Researchers sometimes describe the effect as resetting the sympathetic nervous system.
The procedure typically takes 5 to 15 minutes and is performed using ultrasound guidance to ensure precise placement of the injection.
REPORTED SUCCESS RATES
Me!, as well as ...
Studies and clinical reports demonstrate the treatment provides meaningful relief for many patients suffering from trauma‑related symptoms.
Research cited in trauma medicine literature reports success or improvement rates ranging from approximately 70 percent to 90 percent in some patient groups. Other studies report meaningful symptom reduction in roughly half of patients shortly after treatment.
Dr. Mulvaney has treated thousands of patients using ultrasound‑guided SGB injections since 2009. Clinical research involving combat veterans has documented significant improvements in PTSD symptom scores following SGB treatment.
CONTACT INFORMATION FOR DR. MULVANEY’S CLINIC
SGB Treatment Center
Website:
https://sgbtreatmentcenter.com
Phone: 410‑505‑0530
Address: SGB Treatment Center 116 Defense Highway Suite 203 Annapolis, Maryland 21401 United States
STRATEGIC PERSPECTIVE
The emergence of treatments such as the stellate ganglion block reflects a broader shift in trauma medicine. For decades PTSD treatment focused primarily on psychotherapy and medications. New biological approaches such as SGB attempt to address the neurological mechanisms underlying trauma responses.
For war correspondents, soldiers, and first responders alike, these advances signal a growing recognition that the invisible wounds of conflict require both psychological and physiological treatment approaches.
Findings of a 2026 Study
The study titled “War and the Long-Term Psychiatric Health of Journalists Who Cover It,” published in The British Journal of Psychiatry (2026), examined the long-term mental health consequences for journalists who reported from conflict zones following the September 11, 2001 attacks through the period surrounding the Arab Spring (2001–2013).
The authors sought to determine whether prolonged exposure to war environments created measurable psychiatric effects similar to those documented among soldiers, first responders, and other high-risk professions. The central research question was whether war correspondents experience higher rates of psychiatric disorders compared with journalists who do not cover war.
The study concluded that journalists covering modern conflicts face psychiatric risks comparable to those experienced by military personnel and other trauma-exposed professions. War reporting was found to be a hazardous occupation not only physically but psychologically.
Researchers emphasized that the elevated prevalence of PTSD, depression, anxiety disorders, and alcohol misuse demonstrates the need for institutional mental health support for journalists assigned to conflict zones.
FINAL NOTE: CHECKING ON YOUR BATTLE BUDDIES
There is also a personal responsibility that extends beyond institutions. Anyone who has deployed alongside soldiers, Marines, airmen, special operators, or fellow correspondents knows the importance of looking out for the people who shared those experiences.
Pick up the phone and call someone you served or reported with. Do not begin by asking if they are struggling. Start by telling them how you are doing and why you are doing fine. That simple opening often gives them permission to speak honestly.
If something in their voice or behavior raises concern take it seriously and say something.
Help exists.
Organizations now specialize in treating trauma among journalists and veterans alike. But none of that support can begin unless people overcome the stigma of self-reporting, and step forward. Be the friend that nurtures that forward.